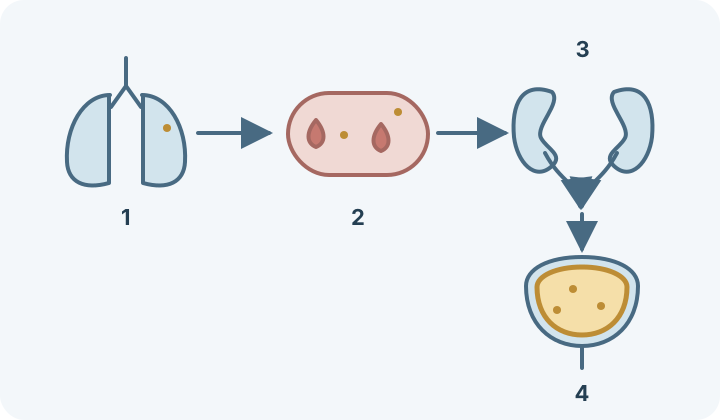
The gold dots represent substances, not tumour cells. Arrows show a possible transport and excretion route; they do not show dose, timing or an inevitable cancer sequence.
- 1 · Inhalation
Some smoke chemicals enter blood through the lungs.
- 2 · Circulation
Blood carries substances beyond the lungs.
- 3 · Urine
Some substances or their metabolites are excreted by the kidneys.
- 4 · Contact
Urine meets the bladder lining; carcinogens can damage DNA.
The bladder stores urine, not inhaled smoke
The kidneys make urine, which travels down the ureters to the bladder before leaving through the urethra. This separates the route of air from the route of urine: smoke does not have to travel down an airway into the bladder.
Cancer-causing substances, or products formed as the body processes them, can reach urine after entering the bloodstream. Contact with the lining can damage cell DNA. Kidney clearance means a substance is being moved out of blood; it does not make every part of that route harmless.
Why the lining matters
Most bladder cancers arise in urothelial cells lining the inside of the bladder. Urothelium also lines other parts of the urinary tract, including the ureters and renal pelvis. ‘Urinary tract’ names a connected system, not a claim that every cancer in it has an identical cause or risk.
Cell type and depth answer different questions
Imagine a general explanation containing both ‘urothelial carcinoma’ and ‘non-muscle-invasive’. The first describes the cells from which the cancer arose; the second says it has not grown into the bladder's muscle layer. They are not competing names for the same feature.
Muscle-invasive disease describes growth into that muscle layer. Neither depth nor cell type identifies the cause of an individual tumour. These distinctions are useful vocabulary, not instructions for interpreting a personal pathology report.
A cause is not the whole story of every case
Smoking is an important risk factor, but people who have never smoked can also develop bladder cancer. Other influences include certain chemical exposures and family or medical history. An occupational label by itself does not establish someone's exposure.
For personal urinary concerns or a report, use qualified medical care; in England, the NHS identifies the GP as a route for assessment. Explaining urine contact does not establish a water-drinking, ‘detox’ or screening plan. Such decisions require clinical context.
What to keep in mind
Sources
The central claims on this page were checked against the sources below.
- National Cancer Institute: Bladder cancer: smoking, blood and urine
Sources checked: 2026-10-10
- National Cancer Institute: Bladder anatomy, urothelial cells and muscle invasion
Sources checked: 2026-10-10
- NHS: Bladder cancer causes and GP care
Sources checked: 2026-10-10
Population-level education, not diagnosis, personal risk estimation, report interpretation, screening eligibility or a treatment plan. Individual decisions belong with qualified local healthcare professionals.