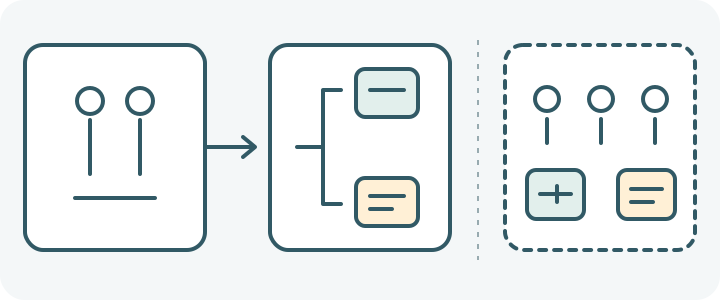
A schematic of study design, not a risk curve. The separate group is the newer urban cohort; it is not a later recovery stage of the women in the first study.
- Entry in the women's study
No known coronary disease when participants joined.
- Status before the event
Follow-up separates those with and without known coronary disease.
- A different urban cohort
The 2026 study includes prior cardiovascular disease and compares with never smokers.
The outcome is a death, not a lower pulse reading
Sudden cardiac death is an unexpected fatal event assessed as cardiac in origin. Cardiac arrest is the abrupt loss of effective heart function; it can be survived, so a cardiac arrest count and a death count are not interchangeable. A heart attack is also a different event, although it can lead to arrest. The quitting studies below do not measure success at resuscitation.
A resting pulse that has fallen after quitting is not a measurement of sudden death risk. Nor does having no coronary diagnosis establish that the heart has no disease. A research estimate cannot evaluate a current cardiac concern or identify its cause. That needs qualified medical assessment; the number of days without cigarettes supplies neither a diagnosis nor reassurance that a problem is resolved.
In the women's study, ‘without coronary disease’ has two meanings
A 2012 study followed 101,018 women who had no known coronary heart disease at entry. Women who developed it later were not simply removed from the main analysis. The researchers then separately considered whether coronary disease had been diagnosed before a sudden cardiac death. Entry criteria and a later subgroup are therefore different filters.
In the subgroup without known coronary disease before the event, stopping for less than five years was associated with a hazard ratio of 0.46 compared with current smoking; the 95% confidence interval was 0.24–0.91. A hazard ratio compares event rates among people still at risk during follow-up, not the percentage of people who will die. This broad interval of quitting duration does not identify the first day or week of a change. The study was observational, relied on reported smoking status and mainly involved white female nurses; it cannot supply the same numerical prediction for every reader.
A newer urban cohort is useful, but not the same population
The 2020 Surgeon General report judged the evidence for quitting reducing sudden cardiac death in people without coronary disease suggestive, but not sufficient for a causal conclusion. That is the report's dated assessment, not a statement that later research does not exist. A Danish urban cohort published in 2026 adds observational evidence, but includes people with previous cardiovascular disease. It is not a new study exclusively of people without coronary disease.
In that study, people who had stopped 26–67 years earlier had a hazard ratio of 1.02 versus never smokers, with a 95% confidence interval of 0.75–1.38. This does not prove the groups equivalent or make year 26 a personal reset date. It also uses never smokers as the reference, unlike the women's subgroup comparison with current smokers. The primary analysis used smoking status at baseline; updating it at a later visit was a sensitivity analysis. Different populations, reference groups and methods prevent stitching these numbers into a single recovery countdown.
A useful takeaway does not need an exact safe date
Quitting is worth pursuing without promising that it abolishes sudden cardiac death. If a headline says ‘risk returns to normal’, ask three things: normal compared with whom, for which outcome, and in which people? A study average cannot decide whether you need testing, what exercise is safe or whether prescribed care should change. Those questions belong with a qualified clinician.
For support in England, the NHS describes local stop-smoking services; elsewhere use the relevant local health service. Help with quitting and assessment of a cardiac concern are different appointments, and a smoke-free milestone does not confirm that a concern has resolved. You do not need to put a smoking history, pulse reading or family history into an online risk form here.
What to keep in mind
Sources
The central claims on this page were checked against the sources below.
- U.S. Department of Health and Human Services / NCBI Bookshelf: Smoking Cessation (2020), Chapter 4: sudden cardiac death and cardiovascular conclusions
Sources checked: 2026-10-08
- Circulation: Arrhythmia and Electrophysiology: Sandhu et al. (2012): Smoking, smoking cessation and sudden cardiac death; Methods, Table 4 and limitations
Sources checked: 2026-10-08
- Scientific Reports: Isozaki et al. (2026): Smoking and sudden cardiac death in an urban population; accepted manuscript, Methods, cessation results and Figure 3
Sources checked: 2026-10-08
- American Heart Association: Cardiac arrest: definition and occurrence with or without diagnosed heart disease
Sources checked: 2026-10-08
- American Heart Association: Cardiac arrest: explanatory background, not a personal risk estimate; updated August 2026
Sources checked: 2026-10-08
- NHS: England: local stop-smoking services
Sources checked: 2026-10-08
General interpretation of population research, not an individual sudden death estimate, diagnosis, testing decision, exercise clearance or change to medical care.