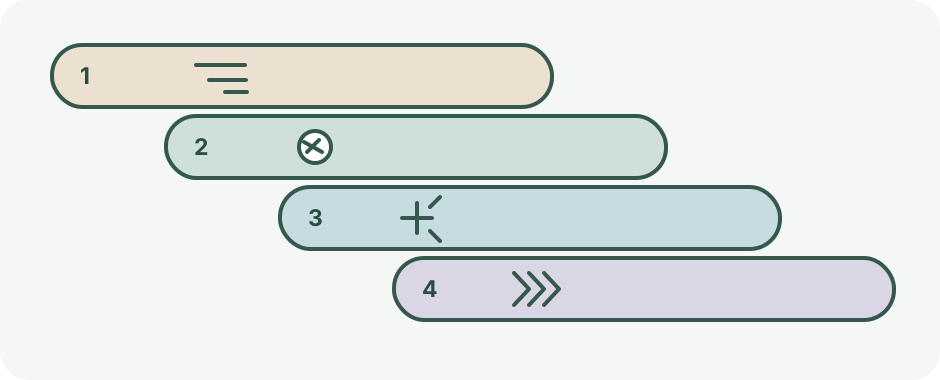
Conceptual overlap only. Width, spacing and order do not specify days, speed or a wound's current stage.
- 1 — Haemostasis
A temporary clot is formed.
- 2 — Inflammation
Immune cells organise cleanup and responses.
- 3 — Proliferation
New tissue and vessels are built.
- 4 — Remodelling
The supporting matrix is reorganised.
Four overlapping jobs keep repair moving
Basic physiology describes haemostasis, inflammation, proliferation and remodelling. In plain language: forming a temporary clot, organising immune-cell responses and cleanup, building new tissue and vessels, then reorganising the tissue's supporting matrix. These processes overlap rather than switching on and off in four sealed boxes.
This matters because a wound looking closed does not mean every repair process is complete. The diagram explains coordination only: its band lengths are not days, expected recovery speeds or instructions for assessing a wound.
Oxygen and cells contribute in different ways
The 2012 mechanism review describes reduced tissue oxygenation and changes in inflammatory-cell movement and bactericidal functions. It also describes reduced fibroblast migration and proliferation, with lower collagen synthesis and deposition. Fibroblasts help build supporting tissue; oxygen supply alone is not the whole explanation.
The review examines smoking, nicotine and nicotine-replacement therapy separately. Findings about smoke exposure do not justify treating those exposures as interchangeable or choosing, stopping or changing a medicine yourself.
What does a clinical study count as a complication?
The 2012 clinical review compared smokers and nonsmokers in 140 cohorts of surgical patients. It classified delayed healing and separation, surgical-site infection, necrosis and other outcomes separately. Such studies concern postoperative populations, not a prediction for every minor cut or every operation.
Imagine two fictional reports: one records an incision that separated, another records a surgical-site infection. Both discuss wound complications, but they have not counted the same event. Even a shared relative measure would need its specific comparator, event and study population before interpretation.
These observational cohorts also differed in how smoking and healing were defined, and outcome assessment and follow-up were not always clear. Other clinical factors could affect the comparisons, so the group association does not establish that smoking caused every difference.
Bring the right question to the people managing the wound
You could ask your clinical team: ‘When you say smoking affects healing, which outcome is relevant here, and what support can you arrange?’ This keeps the discussion connected to the actual wound or planned procedure, without substituting an online timetable for their assessment.
If a wound is concerning or deteriorating, contact the responsible clinical team or appropriate local care; urgent danger uses local urgent or emergency services. For cessation support in the United States, CDC lists public routes. That support complements rather than replaces wound care; this page gives no dressing instructions or surgery-delay recommendation.
What to keep in mind
Common questions
Is a closed wound necessarily fully repaired?
No. Surface closure and the entire repair process are not identical; remodelling is one of the overlapping processes. The diagram cannot determine the state of your wound.
Can this research tell me when it is safe to have surgery?
No. Different procedures, people and outcomes cannot be reduced to one smoking countdown. Timing and preparation belong to the clinical team, not to a date calculated from this article.
Sources
The central claims on this page were checked against the sources below.
- StatPearls / NCBI Bookshelf: Physiology, Wound Healing — updated 2025-04-04
Sources checked: 2026-10-02
- Annals of Surgery / NCBI PubMed: Wound healing and infection in surgery: the pathophysiological impact of smoking, smoking cessation, and nicotine replacement therapy: a systematic review — June 2012; mechanism abstract
Sources checked: 2026-10-02
- Archives of Surgery / JAMA Network: Wound Healing and Infection in Surgery: The Clinical Impact of Smoking and Smoking Cessation: A Systematic Review and Meta-analysis — April 2012
Sources checked: 2026-10-02
- World Health Organization: Smoking greatly increases risk of complications after surgery — 2020-01-20; oxygen, immune function and healing
Sources checked: 2026-10-02
- US Centers for Disease Control and Prevention: How to Quit Smoking — reviewed 2024-09-27
Sources checked: 2026-10-02
General tissue-repair and postoperative group evidence. No wound diagnosis, individual risk estimate, home-care procedure, medicine advice or surgical timetable. Personal concerns belong with the responsible clinical team.